If you don't know which campaign produced which surgery, you're managing ad budget on instinct. How to build the chain without breaking it.
Most clinics measure advertising by cost per lead. That's only the first link in the chain. The real question is: which campaign, from which country, for which treatment, produced how much revenue? A clinic that can't answer it keeps pouring budget into campaigns that deliver cheap leads and no surgeries.
The links in the chain
- Source, campaign and creative must be written to the CRM together with the lead.
- Treatment area and country should be tagged at first contact.
- Pipeline stages need money attached: quote value, deposit, remaining balance.
- Loss reasons must come from a fixed list; free text can't be analysed.
- Booking and surgery dates belong in the system so delayed conversions stay visible.
The delayed conversion problem
A patient can see an ad in March and have surgery in June. A 30-day attribution window in the ad platform never sees that, so you switch off a campaign that was actually working. When the lead source is stored permanently in the CRM, June's revenue is credited to March's campaign. In medical tourism the right attribution window is 90–180 days, not 30.
Three reports a manager should read weekly
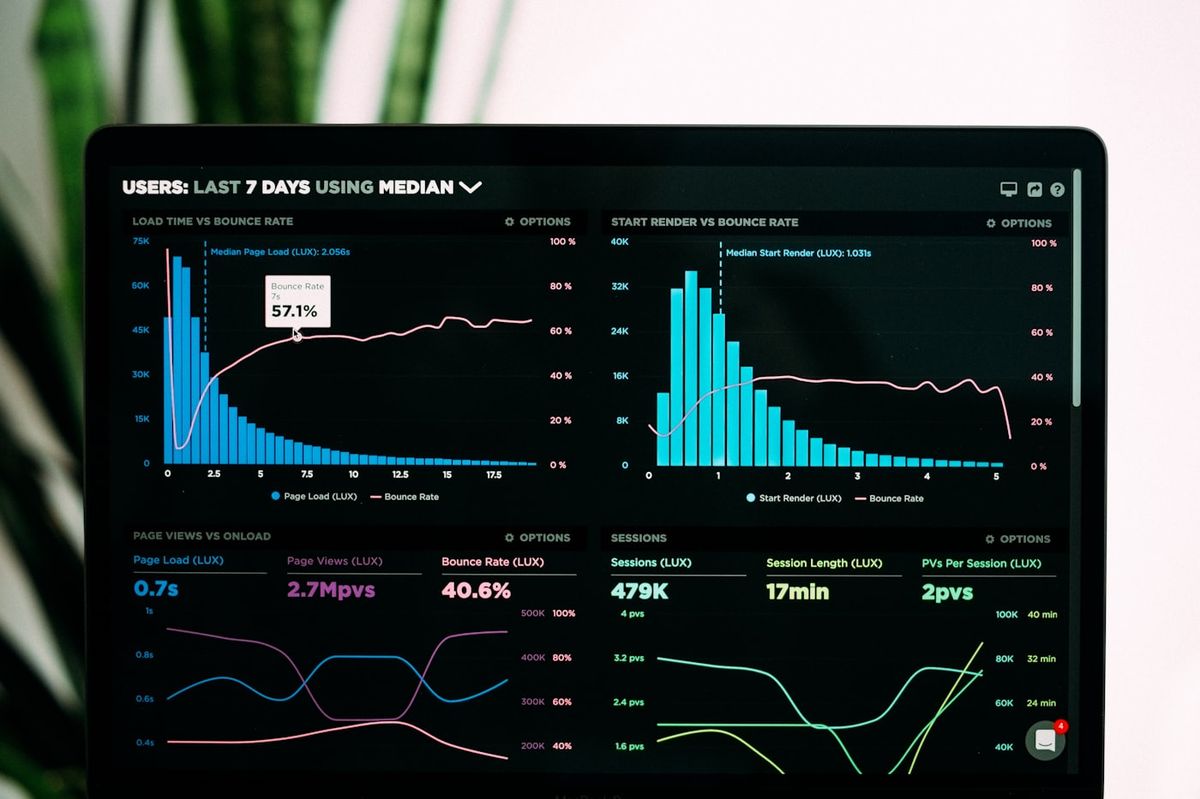
First, the funnel by source: how many leads, quotes and bookings. Second, response time and conversion rate by agent. Third, average basket and margin by treatment. Read together, those three take budget decisions out of the realm of opinion.
“Ad budget should flow to the channel that produces the most surgeries, not the cheapest leads. They are rarely the same channel.”
Building the chain isn't technically hard; the hard part is getting the team to enter data consistently. So keep fields few, standardise the options, and automate every step you can. Data that never gets entered is data that doesn't exist.
The only CRM built for medical tourism
Bring your whole medical tourism operation into one panel — without paying per user.
Book a free demo

